Tunnelled central line (Hickman)
A long-term central line tunnelled under the chest skin, usually for chemo or TPN. The default assumption in a febrile patient is that the line is infected - but prove it and don't reflexively remove it.
Also called: Hickman, Hickman line, tunnelled CVC, tunnelled central venous catheter, Broviac, Groshong, skin-tunnelled line
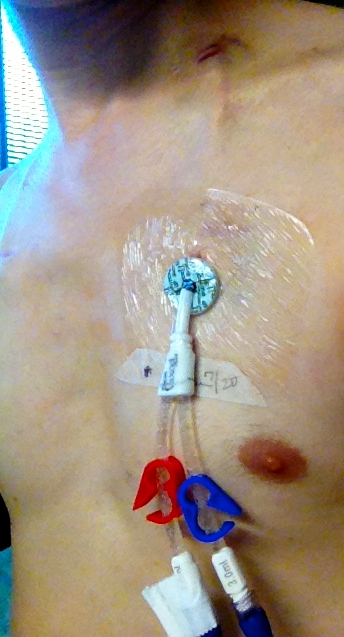

What it is
A tunnelled central venous catheter exits the skin on the chest wall, runs a few centimetres under the skin (the tunnel) and then enters a central vein, with a cuff in the tunnel that tissue grows into to anchor it and act as an infection barrier. It is for long-term use - chemotherapy, long-term TPN, or frequent access. epic3 recommends Use a tunnelled or implanted central venous access device with a subcutaneous port for patients in whom long-term vascular access is required
.
The ED-relevant problems are infection (exit-site, tunnel or bloodstream), occlusion/breakage, and dislodgement. Used in adults and children (paediatric oncology Hickman and Broviac lines are common); principles are the same, with the child's team directing care.
How to recognise it
- A catheter exiting the chest wall, often with a cuff palpable in the tunnel, one or more lumens, and a clamp on each lumen.
- A patient on chemotherapy or home TPN, carrying line-care information.
- Exit-site infection (redness, discharge, tenderness at the skin exit), tunnel infection (tenderness and erythema tracking along the tunnel), or signs of bloodstream infection (fever, rigors, often with the line).
What it gets confused with
A port-a-cath is fully implanted under the skin with nothing exiting the body - you see and feel a disc, not a protruding catheter. A Hickman has an external catheter you can see. Both are long-term chest devices.
A tunnelled dialysis catheter is a large-bore tunnelled chest line too, but it is the patient's dialysis lifeline, locked with heparin or citrate, and must not be used for routine bloods or drugs. A Hickman is a smaller general-purpose line. Check what the line is for before using it.
What goes wrong
Catheter-related bloodstream infection
Fever or rigors in a patient with a tunnelled line, with or without local signs. This is the default assumption until excluded.
Red flag
Take blood cultures before antibiotics - and from a tunnelled line, take a set from the line as well as peripherally, so the line can be implicated or cleared as the source. Treat sepsis; involve the owning team on whether the line stays.
Exit-site or tunnel infection
Exit-site: redness, discharge and tenderness at the skin. Tunnel: tenderness and erythema tracking along the subcutaneous course, which is more serious.
Red flag
A tunnel infection or an exit-site infection with systemic features is more likely to need line removal than a simple exit-site infection. Culture, start antibiotics per local policy, and refer.
Occlusion, breakage or dislodgement
Will not flush/aspirate; a split or leaking catheter; or a line that has partly pulled out.
Red flag
A split central line risks air embolism - clamp between the break and the patient and stop using it. A line that has pulled out needs an occlusive dressing and firm pressure over the entry site. If the patient becomes acutely breathless or shocked, suspect air embolism - head-down on the left side, high-flow oxygen. Do not force a blocked lumen.
The first ten minutes
- Assess and treat the clinical problem (sepsis, neutropenia, the presenting complaint) first.
- Suspected line sepsis: cultures before antibiotics where possible (peripheral, plus a set from the line if it is immediately available) - but never hold antibiotics in neutropenic sepsis or septic shock to get the line sample - then start sepsis/neutropenic-sepsis treatment per policy.
- Access the line only with strict asepsis - aseptic technique and hub decontamination for at least 15 seconds - and flush only with sterile saline.
- Clamp and stop using a split or dislodged line; refer.
- Call the owning team (oncology, nutrition, vascular access) about the device and whether it needs to come out.
Do not
Who owns it
The team that uses the line - oncology/haematology, nutrition, or vascular access. Tell them the device, the local and systemic findings, the culture results, and whether the line still works.
Who to call
The team and the criteria are national. The phone number is local, and this tool does not know it. Find it once, now, and write it on the department's own card — that is the part no website can do for you.
- Say the device name first
- Open with laryngectomy, LVAD, shunt — the single word changes who comes and what they bring. Do not bury it in the history.
- Say what you have already established
- Whether the device is patent, whether it has been removed or disturbed, and what you have already tried. The specialist is deciding whether to walk or run.
- Ask who owns it out of hours
- Device ownership and the on-call route often differ from the implanting specialty, and it is frequently a regional centre rather than your own hospital.
- The patient's own team is a resource, not an afterthought
- Named nurse specialists, home-care companies and device helplines answer questions nobody else can, and the patient usually has the number.
When the device is not the problem
A patient with a device gets pneumonia, sepsis, pulmonary oedema and myocardial infarction at the same rate as everybody else. The device is the most visible thing about them and it attracts the whole assessment.
- The NTSP says it out loud
- The project's own manual warns that
patients with tracheostomies can become unwell with all the problems that other patients get too. It is easy to become fixated with the tracheostomy.
The same sentence applies to every device in this tool. - Clear the device, then leave it
- Establish that the device is doing its job — the stoma is patent, the line draws back, the pump is running — and then assess the patient as you would anyone else.
- The anchoring runs both ways
- The opposite error is treating a device complication as a medical illness: a blocked gastrostomy read as vomiting, a baclofen pump failure read as sepsis.
- NTSP manual — Red flags · read in full
What the patient will be carrying
Patients carry a line passport with the device, insertion date and the owning team's contact, and many know their line-flushing routine. Ask for it.
Scope of this page
This page covers recognising a tunnelled central line and the first ED steps for infection, occlusion and breakage: culture, treat, access aseptically, refer. It does not cover line insertion, exchange, thrombolytic unblocking, or the definitive decision to remove, which belong to the owning and vascular access teams. Used in adults and children; paediatric care is team-directed.